
Privacy Disclosure Statement
Astelin
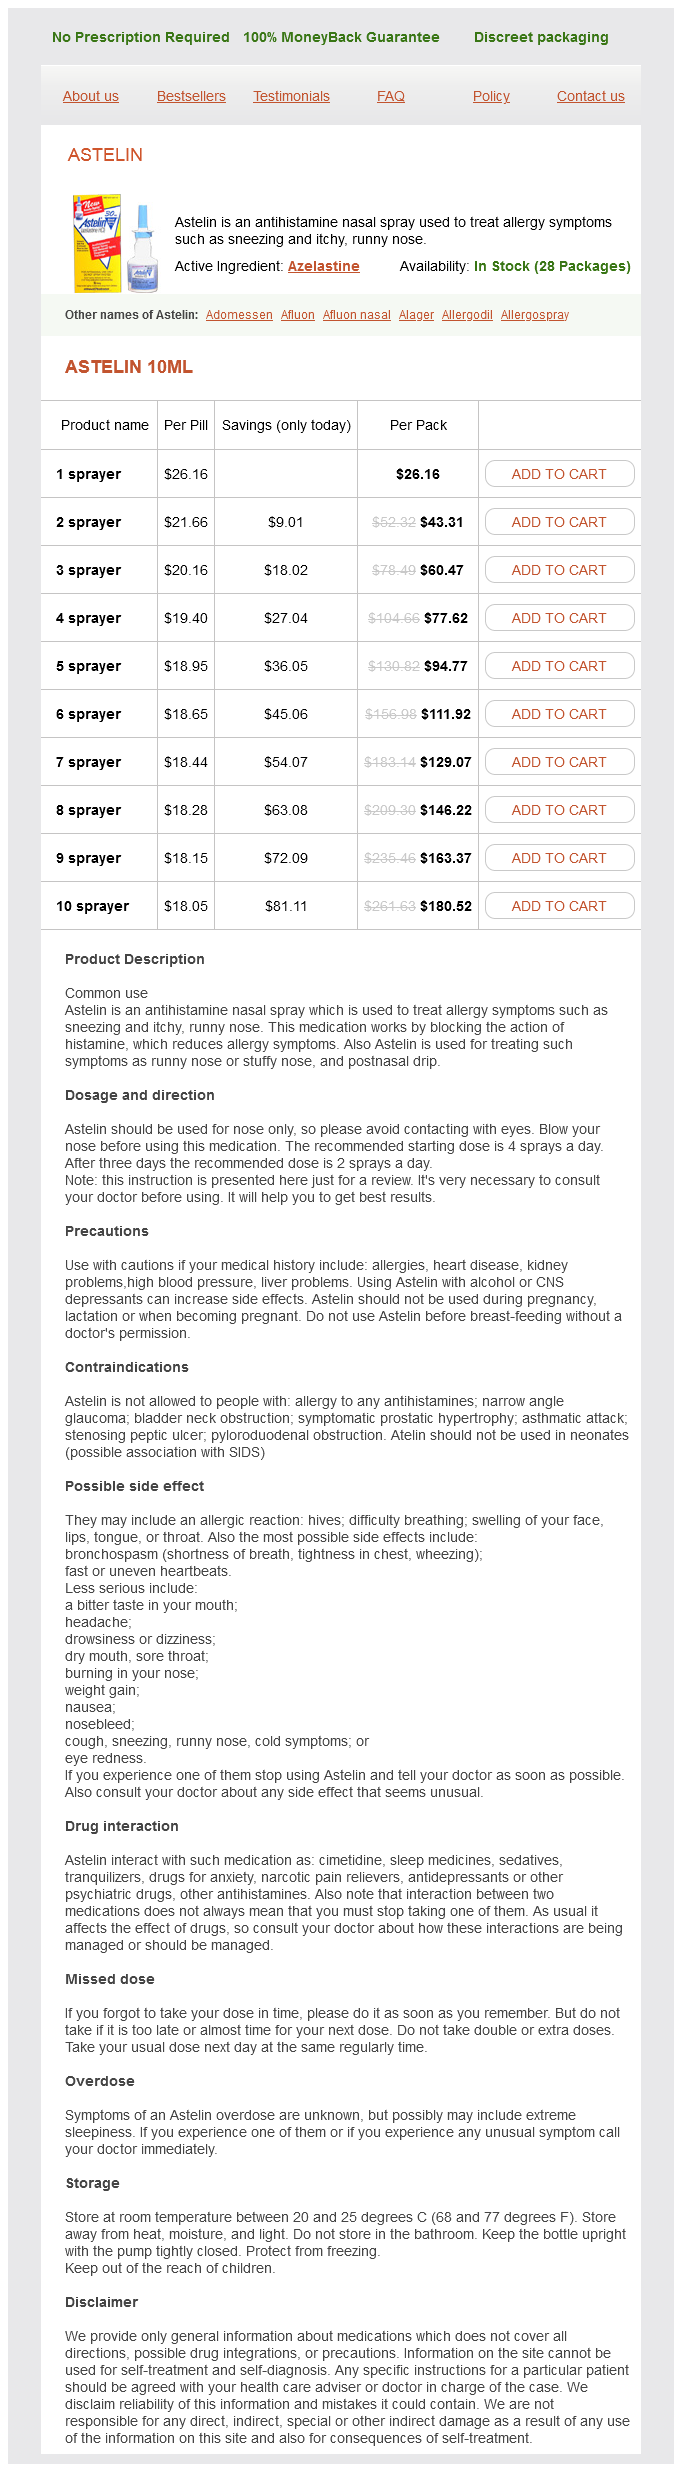
Astelin 10ml
- 1 sprayer - $26.16
- 2 sprayer - $43.31
- 3 sprayer - $60.47
- 4 sprayer - $77.62
- 5 sprayer - $94.77
- 6 sprayer - $111.92
- 7 sprayer - $129.07
- 8 sprayer - $146.22
- 9 sprayer - $163.37
- 10 sprayer - $180.52
Astelin dosages: 10 ml
Astelin packs: 1 sprayer, 2 sprayer, 3 sprayer, 4 sprayer, 5 sprayer, 6 sprayer, 7 sprayer, 8 sprayer, 9 sprayer, 10 sprayer
Only $19,18 per item
In stock: 692
Description
Bell palsy treatment with acyclovir and prednisone compared with prednisone alone: a doubleblinded allergy forecast phoenix az astelin 10 ml generic otc, randomized controlled trial allergy university of iowa astelin 10 ml quality. Endoscope assisted surgical procedure of the trigeminal allergy treatment local honey cheap astelin 10 ml mastercard, facial allergy symptoms breathing astelin 10 ml generic free shipping, cochlear or vestibular nerve. Trigeminal neuralgia: problems as to trigger and consequent conclusions concerning therapy. Trigeminal neuralgia treated by microvascular decompression: a long-term follow-up study. Posterior fossa reexploration for persistent or recurrent trigeminal neuralgia or hemifacial spasm: surgical findings and therapeutic implications. Total facial nerve decompression in recurrent facial paralysis and the Melkersson�Rosenthal syndrome: a preliminary report. A comparative research of the fallopian canal at the meatal foramen and labyrinthine phase in younger kids and adults. Labyrinthine section and geniculate ganglion of the facial nerve in fetal and grownup temporal bones. Pathologic findings within the labyrinthine segment of the facial nerve in a case of facial paralysis. Surgical exposure of the internal auditory canal and its contents by way of the middle cranial fossa. Hypoglossal-facial nerve interpositional leap graft for facial reanimation with out tongue atrophy. Facial reanimation with jump interpositional graft hypoglossal facial anastomosis and hypoglossal facial anastomosis: evolution in administration of facial paralysis. Temporalis muscle for facial reanimation: a 13-year expertise with 224 procedures. Temporalis tendon switch as a half of a complete strategy to facial reanimation. Long-term follow-up of nerve conduction velocity in cross-face nerve grafting for the remedy of facial paralysis. Free neurovascular muscle transposition for the treatment of facial paralysis using the hypoglossal nerve as a recipient motor supply. It became obvious that probably the most direct method to sure inaccessible intracranial tumors was through the cranium base quite than by way of the calvarium. Therefore, in the first half of the twentieth century, surgeons avoided the complexity of the cranium base and most popular the simpler solution of working by way of the skinny calvaria, despite the precise fact that injurious levels of brain retraction have been often required. In the 1960s, William House and others utilized modern working microscopes and high-speed drills to resurrect a number of skull-base approaches that had previously been deserted as impractical. The term skull base surgical procedure is considerably of a misnomer, as only a few surgical procedures are actually carried out to resect lesions intrinsic to the cranium base. In reality, the overwhelming majority of neurotologic skull base procedures are performed for lesions positioned beneath the cerebral cortex or adjoining to the brainstem, and the removing of bone permits exposure while minimizing cerebral and cerebellar retraction. This chapter will focus on the posterior fossa which is bordered by the clivus anteriorly, the posterior floor of the petrous portion of temporal bones laterally and the occipital bone posteriorly. It is bordered by the posterior surface of the temporal bone anteriorly, the anterior surface of the cerebellum posteriorly, the inferior olive medially, the inferior border of the pons and cerebellum superiorly, and the cerebellar tonsil inferiorly. The petrous apex is pyramidal in form, with anterior, posterior, and inferior surfaces. The anterior floor types a portion of the center cranial fossa and the posterior floor marks the anterolateral extent of the posterior fossa. The lateral extent of the petrous apex is demarcated by the inside ear and intratemporal portion of the carotid artery. Medially, the posterior floor ends on the petroclival and petrooccipital synchondroses, the place it abuts the clivus. Traditionally, the jugular foramen is described as having a posterior vascular compartment, pars venosa, and an anterior neural compartment, pars nervosa, that are separated by a fibrous or bony bridge connected to the jugular spine. These tumors involve the skull base either via primary development, direct extension from adjacent websites, or by metastatic unfold. Note that a loop of the anterior inferior cerebellar artery often traverses between the facial and vestibulocochlear nerves at their brainstem entry site. This loop sometimes offers off a department that enters the internal auditory canal and provides the inner ear. These clinical findings could be organized based mostly upon cranial nerves affected, brainstem and cerebellar compression, hydrocephalus, and direct invasion of structures. The clivus is a portion of the occipital bone that extends from the anterior margin of foramen magnum to the dorsum sellae. Preoperative hearing ranges are useful in deciding on the surgical method (hearing conservation versus nonconservation) and might have prognostic worth when a hearing conservation strategy is being considered. The combination of pre- and post-gadolinium enhanced T1-weighted (T1W) photographs, T2-weighted (T2W) photographs, diffusion scanning, and fat suppression methods helps to differentiate between varied problems Table 35-3). Angiography and endovascular techniques can be utilized within the evaluation of vascular lesions similar to aneurysms, arteriovenous malformations, dural arteriovenous fistulas, and jugulotympanic glomus tumors. These lesions might have heterogeneous enhancement secondary to non-enhancing microcystic and macrocystic components within the tumor. However, tumor extension into the labyrinthine section of the Fallopian canal, as manifested by enlargement or enhancement, is usually a helpful distinguishing factor between the two entities. Central +/- Hydrocephalus Cerebellar indicators Headaches Papilledema Diplopia Anosmia Seizures Long-tract Sensory and/or Motor Dysfunction Modified after Jackler and Driscoll. Adjacent dural thickening, often known as the dural tail or meningeal sign, is found in 60% of circumstances and often represents reactive thickening somewhat than neoplastic change. Hyperostosis of adjacent osseous structures, although rare, can be a very reliable indicator of meningioma. Therefore, they typically insinuate into various cisterns and have irregular margins that are scalloped or "cauliflower-like". Rarely, "white epidermoids" might show reversed sign traits with a high T1W and low T2Wsignal. Petrous apex effusions, mucoceles, and ldl cholesterol granulomas are essentially the most generally encountered radiographic abnormalities encountered in the petrous apex and are thought to characterize factors alongside a continuum of pathology. Incidental petrous apex effusions are often mistaken for disease with a variable T1W signal and a excessive T2W signal. Mucoceles are typically darkish on T1W photographs, bright on T2W images, and have peripheral rim enhancement. Irregular "scalloped margins" are more suggestive of epidermoid cysts, while clean margins are more characteristic of 1549 mucoceles or ldl cholesterol granulomas. Solid lesions of the petrous apex include metastasis, plasmacytoma, and endolymphatic sac tumors. These lesions usually trigger bone destruction and show variable degrees of central enhancement on postcontrast imaging. A unique function of endolymphatic sac tumors is the presence of intralesional calcifications within the retrolabyrinthine area alongside the posterior semicircular canal. Bony lesions together with fibrous dysplasia, Paget disease, and osteoradionecrosis must also be thought of in the differential analysis of temporal bone lesions. Occasionally, asymmetric pneumatization of the petrous apex could be mistaken for pathology. Chordomas are midline lesions that come up from notochordal remnants near the sphenooccipital synchondrosis. Chondrosarcromas come up from cartilage, generally the petroclival synchondrosis, and are normally off the midline. These lesions may be differentiated from osseous metastases, which regularly trigger a decrease in normally hyperintense T1W and T2W marrow signal. Pituitary macroadenomas could cause enlargement of the sella with sometimes easy bony growth. However, once the tumor has transgressed the bone, the lesion might mimic a clival malignancy. The radiographic differentiation of these subtypes is straightforward when the lesions are small and remain confined to their web site of origin. Erosion of the lateral bony plate of the jugular fossa favors the prognosis of a glomus jugulare.
Ayuk Willku (Maca). Astelin.
- What other names is Maca known by?
- >Anemia, leukemia, chronic fatigue syndrome (CFS), enhancing energy and athletic performance, improving memory, depression, female hormone imbalance, menstrual problems, infertility, menopause symptoms, osteoporosis, stomach cancer, tuberculosis, sexual problems, immune system stimulation, AIDS, and other conditions.
- What is Maca?
- Enhancing sexual desire in men.
- How does Maca work?
- Are there safety concerns?
- Dosing considerations for Maca.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96554
First allergy symptoms bloody nose astelin 10 ml generic, the patients being chosen for observation in these research may characterize those with a extra indolent course allergy to grass treatment trusted 10 ml astelin, thereby introducing a selection bias allergy treatment kids 10 ml astelin buy. Second allergy medicine xyzal 10 ml astelin visa, these slow-growing tumors might not present important development when followed for only three years, whereas their progress might turn out to be apparent if they had been adopted over the long-term (eg, 10 to 20 years). Finally, strategies used to measure tumor 1560 measurement remain somewhat inexact, making comparison troublesome. Most experts have simplified this to the single largest measurement in the axial aircraft. A long-term study from Denmark overcame many of these obstacles by following sufferers over 30 years and by measuring the extrameatal tumor in a constant style. It was discovered that 1% of tumors decreased in dimension, 70% remained steady, and 29% demonstrated development. The growth incidence or fee was not associated to either gender or age of the patients. The natural development of those symptoms based mostly on tumor size is summarized in Table 35-6. Historically, the relative frequencies of varied symptoms have changed with the evolution of improved imaging modalities, which has allowed earlier prognosis. Patients will usually complain of poor clarity, as word recognition is affected out of proportion to pure tone hearing loss. Note the compression of the lateral facet of the pons, indentation of the cerebellar peduncle, and displacement of the trigeminal nerve. The tinnitus is usually constant, high-pitched and localized to the affected ear, however it could have variable qualities and be non-localizing. This is most likely going because of the gradual destruction of vestibular operate, which permits central adaptation to happen. When present, vertigo typically occurs from small tumors, affecting ears during which appreciable vestibular function remains. Disequilibrium is the continual sense of instability which is commonly secondary to an uncompensated peripheral vestibular disturbance and/or cerebellar compression. Trigeminal nerve dysfunction typically presents as midface hypesthesia or parathesia and eventually progresses to contain different divisions of the face. Trigeminal symptoms usually happen within the brainstem compressive stage when the trigeminal nerve becomes stretched and compressed superiorly. The corneal 1563 reflex is kind of all the time decreased or absent in these patients, and this signal might precede any sensory facial disturbance. When present, it usually manifests as unilateral temporal losing, masseter atrophy, and secondary malocclusion. Facial nerve dysfunction may present as both hypofunction (weakness or paralysis) or hyperfunction (twitch, spasm). Clinically detectable weakness of the nerve could happen in massive tumors, however the incidence is lower than 2%. Facial hyperfunction is independent of tumor dimension and can co-exist with facial weak spot. Minor twitching of the face, generally seen in the orbicularis oculi muscle, can occur in as a lot as 10% of sufferers. Table 35-7Clinical Manifestations of Vestibular Schwannoma Symptom Cushing (1917)198 Selesnick (1993)48 Matthies (1997)46 Hearing Loss 100 percent 85% 95% Tinnitus 56% 63% Disequilibrium 48% 61%a Vertigo 19% 61%a Trigeminal nerve 63% 20% sixteen. The nystagmus within the horizontal airplane usually beats away from the tumor facet indicative of ipsilateral vestibular hypofunction. However, with larger tumors, a vertical airplane nystagmus may be seen because of brainstem compression. Chronic elevated intracranial pressure may trigger optic atrophy which is characterised by a progressive loss of peripheral vision and eventual blindness. When present, such dysfunction ought to prompt the reevaluation of the prognosis, and a jugular foramen schwannoma must be considered to be extra likely. The audiogram configurations are variable, and one research revealed a down-slope in 68%, a trough in 9%, flat in 9%, low frequency in 8%, a peak form in 5%, and normal in 1%. Although the sensitivity and specificity of those exams is poor, irregular results could also be an indication for further investigations. In common, higher preoperative hearing is related to higher rates of hearing preservation. Therefore, an absent caloric response indicates harm to the superior vestibular nerve, and occurs more incessantly from tumors originating from the superior vestibular nerve itself. Gadolinium-enhanced scans can then be acquired if the screening is indeterminate, or if different inflammatory/neoplastic processes are suspected. The objectives in administration are first the preservation of life, second the preservation of facial perform, and third the preservation of hearing. Of course, the dangers and benefits of each of the therapy options should be discussed with the patient on this collaborative decision-making process. Therefore, unfavorable patient lifespan factors (advanced age, infirm health) and 1568 favorable tumor factors (small measurement, steady, or slow-growing) are considered indications for conservative management. Disadvantages to selecting statement embrace: 1) sufferers may require therapy at a extra superior age thereby raising the danger of issues; 2) some sufferers may require remedy for larger tumors thereby compromising outcomes; 3) the chance for listening to conservation could also be lost with tumor development or listening to deterioration; 4) tumor growth might exceed the boundaries amenable to stereotactic radiation (> three cm); 5) some patients may have important anxiety about having an "untreated" tumor; and 6) the time and expense related to periodic radiologic follow-up. The advantages and downsides of these three approaches have been summarized in Table 35-8. The quantity of tumor removal can be categorised as total removal, near-total removal, or subtotal removal. The experience and talent of the surgeon and perioperative group performs a big role in the choice of surgical approach. Ideally, the surgical staff ought to be comfy with all approaches in order that the choice may be based upon the attributes of the precise affected person and tumor. Infereiorly, the lower cranial nerves (A) are seen, and the jugular bulb (B) has been recognized. The facial nerve (F) takes a variable and infrequently serpentine course throughout the medial side of the tumor. The retractor is engaged over the posterior lip of the petrous bone and retracts the temporal lobe. The facial nerve usually programs across the superior aspect of the tumor floor. The origin of the tumor from either the superior or inferior vestibular nerve is of significance for preservation of each listening to and the facial nerve. The utility of caloric vestibular testing to decide the nerve of origin has been discussed above. In addition, changing the bone plate on the conclusion of the resection can assist in reducing headaches presumably by limiting traction of cervical musculature on the dura. Most sufferers recuperate uneventfully; however, once in a while, the damage may prolong deeply toward the midline and prolonged ataxia could end result. The vestibular disturbance probably reflects abnormal alerts from preserved vestibular nerve remnants which my sluggish vestibular compensation. Individualized remedy depends on numerous elements mentioned above together with hearing standing, radiologic traits (including tumor dimension and geometry), and the potential complications inherent in every approach. Relevant confounding components include tumor size, tumor location, preoperative listening to ranges, surgical strategy, reporting of listening to outcomes, and the definition of success. Conversely, sufferers lacking these favorable characteristics will doubtless have poor results. Stereotactic radiosurgery and radiotherapy are mentioned in Chapter 36, "Stereotactic Radiosurgery and Radiotherapy. Since these tumors are slow-growing, intervention may be typically withheld until tumor growth could be shown on serial imaging. In common, radiotherapy is recommended for smaller tumors in older individuals, whereas younger individuals are really helpful microsurgery no matter tumor dimension. The rationale is that youthful sufferers could have extra time to develop the potential adverse long-term issues of radiation corresponding to secondary neoplasms. Microsurgery is beneficial for larger tumors (>3 cm) as radiotherapy carries the danger of edema and secondary brainstem compressive signs. In our expertise, the recurrence rate following near-total elimination is simply 3%, nevertheless the rate rises to over 30% following subtotal resection. Outcomes of stereotactic radiation for tumor recurrence is much like that of unoperated patients. The gross and microscopic characteristics of meningiomas have been summarized in Table 35-10.
Specifications/Details
The rate of growth of facial paralysis may be speedy if there was an acute infection however may be slow in onset if secondary to gradual enlargement of the cholesteatoma allergy forecast dallas today astelin 10 ml purchase amex. Facial palsies of larger than one year may not show any considerable enchancment after surgical intervention allergy testing methods astelin 10 ml discount otc, and the presence of cholesteatoma will increase the incidence of residual weakness allergy symptoms sweating generic astelin 10 ml online. Subperiosteal Abscess Infection within the mastoid can extend by way of the cortex and type a subperiosteal abscess in the higher neck allergy medicine patch astelin 10 ml cheap on line. There are three principal courses of subperiosteal abscess outlined by their website of formation. In this location, the subperiosteal abscess often, but not persistently, presents with a protuberant auricle, postauricular fluctuance and tenderness, and occasionally spontaneous drainage. These sufferers could complain of, or show signs of, pain along the sternocleidomastoid muscle and have a palpable mass within the infra-auricular region. This is a Bezold abscess and will progress to involve deeper neck areas if not recognized promptly. This might cause preauricular swelling and malocclusion as a outcome of involvement of the glenoid fossa. Ideally, the antibiotics must be started after gram stain and culture is obtained. A myringotomy with tube placement can also be performed to improve ear drainage from the middle ear. A review of patients with a Bezold abscess found that lots of them additionally have other intratemporal and intracranial issues; a immediate mastoidectomy may help stop additional complications. When the pneumatized and marrow containing spaces of the petrous apex turn out to be contaminated, potential routes of drainage can turn out to be obstructed and lead to persistent infection. Even if the center ear and mastoid have been cleared of an infection, the petrous apex should still harbor walled-off an infection. The decrease incidence of acute petrous apicitis as in comparison with mastoiditis is attributable to the decrease incidence of petrous apex pneumatization in the normal situation, which restricts one route of potential extension of an infection. Magnetic resonance imaging, right, reveals local irritation around the cavernous sinus which can cause abducens palsy or trigeminal paresthesias (arrows). Petrous apicitis ought to be suspected if an ipsilateral retro-orbital or deep aural pain persists despite clearance of disease from the middle ear and mastoid. One or extra of these symptoms in association with cochleo-vestibular findings, facial weakness, or signs of systemic infection should immediate cautious evaluation. If drainage of the petrous apex turns into needed, several routes have been defined. These embrace transnasal/transsphenoidal drainage if the anatomy is favorable, although transtympanic infracochlear drainage is the least invasive otologic route. The two principal types of labyrinthitis that may develop are serous labyrinthitis and suppurative labyrinthitis. In distinction, suppurative labyrinthitis is a fulminant bacterial infection throughout the inside ear. Infectious or inflammatory elements in meningitis can follow the cochlear aqueduct to enter the internal ear and result in labyrinthitis ossificans. Mastoidectomy may be needed if the illness persists or progresses to suppurative labyrinthitis. Suppurative labyrinthitis represents invasion of the internal ear by the bacterial organisms. In rare occasions, the labyrinth may require surgical drainage to control intracranial illness. The cochlea on the best (arrowheads) is clearly seen in both photographs, but the left cochlea is ossified and lacks a fluid crammed lumen (arrows). Rather, patients could current with intermittent vertigo or with Tullio phenomenon, during which they report vertigo and oscillopsia with loud noises or aural stress modifications. Signs of a fistula may be evoked clinically by the applying of stress to the ear with pneumatic otoscopy (ie, Hennebert 863 sign). The region of suspected fistula should be approached rigorously, and the cholesteatoma matrix left over the area until the relaxation of the operation is completed. This protects the inner ear from inadvertent suctioning and from the particles created by the drill. Once the remainder of the cholesteatoma and an infection has been removed, the fistula is addressed. Typically, the cholesteatoma can be gently elevated off the membranous labyrinth, and fixed irrigation will stop extra perilymph leakage. A tegmen dehiscence is more widespread in the presence of cholesteatoma and may be related to encephalocele formation. Infection may also unfold hematogenously through venous channels or directly by way of bony dehiscences in the middle- and posterior- fossa plates. The mortality from bacterial meningitis ranges from 5%, to as excessive as 30%, in some collection. The occurrence of meningitis from issues of otitis media or sinusitis portends a worse outcome. More prevalent for meningitis are complaints of fever, neck stiffness, and altered mental standing, which comprise the traditional triad of meningitis. Nuchal rigidity can be assessed by asking the affected person to contact the chin to the chest or to transfer the chin alternately from shoulder to shoulder. Kernig signal is the presence of again or leg ache when the patient is in the supine place and one leg is passively flexed on the hip and then prolonged on the knee. Brudzinski sign can be performed within the supine place and involves passively flexing the neck. A positive signal is the observation of reflexic bilateral hip and knee flexion 865 to carry the legs. These exams are commonly used however appear to have poor sensitivity for detecting meningitis. Cytology shows elevated white cells (generally >100 cells/�L) and increased neutrophils in bacterial meningitis. Microorganisms could additionally be tentatively recognized on gram stain, and the chemistry might demonstrate a low glucose and excessive protein in bacterial infections versus viral meningitis. The cultures can show and determine the microorganism but may show no development if antibiotics have been previously administered. A delay in antibiotic administration could also be related to an elevated mortality. Vancomycin is beneficial to cowl resistant microorganisms however could also be discontinued if tradition and sensitivity so point out. In older patients with out penicillin allergy, ampicillin is really helpful to cover for Listeria monocytogenes, but this is more likely in community-acquired meningitis somewhat than otitic meningitis. Corticosteroids are strongly really helpful early in the course of meningitis to scale back the incidence of subsequent listening to loss and general mortality in kids and adults, respectively. Continued evaluation clinically and radiographically during the course of remedy is critical to identify further issues and ensure that surgical intervention is undertaken expeditiously. Venous Thrombosis Septic thrombophlebitis could impede the venous drainage system coursing through or near the temporal bone. Sigmoid sinus thrombophlebitis is the second most typical intracranial complication of otitis media and has a mortality rate of about 10%. Erosion of bone over the sigmoid sinus and deposition of granulation tissue alongside the vein are commonly seen. Proximal propagation of irritation and clot may involve the transverse sinus and torcula herophili. The thrombus generally progresses to contain one or more of these sites by the point of diagnosis. Presenting symptoms and indicators are variable, and the classic picket fence spiking fevers will not be present. The examination may reveal an intact or perforated tympanic membrane, purulent drainage, edema of the skin of the ear canal, and delicate tissue modifications over the mastoid. Griesinger signal is erythema, edema, and tenderness over the posterior a half of the mastoid process because of septic thrombosis of mastoid emissary veins indicating thrombophlebitis of the 867 sigmoid sinus. In addition to overlaying the similar old aural pathogens corresponding to Streptococcus species and Staphylococcus species, remedy ought to embody protection for mixed flora such as Bacteroides species and Proteus species. Some authors have recommended thrombectomy, ligation, or resection of the sigmoid sinus.
Additional information:
Syndromes
- Pregnancy
- Enzyme assay
- Thromboembolic states
- Radiation therapy (brachytherapy)
- Runny nose
- Poor feeding
- Make sure the blood-acid balance is normal
- Fever and chills
Related Products
Usage: p.c.
Tags: 10 ml astelin proven, buy discount astelin 10 ml online, cheap astelin 10 ml free shipping, 10 ml astelin with mastercard, 10 ml astelin discount fast delivery, buy astelin 10 ml otc, cheap astelin 10 ml visa, astelin 10 ml best, buy astelin 10 ml with visa, astelin 10 ml purchase with amex, 10 ml astelin purchase amex, buy astelin 10 ml otc, buy discount astelin 10 ml on line, purchase 10 ml astelin with amex, astelin 10 ml discount without a prescription, generic astelin 10 ml with visa
9 of 10
Votes: 258 votes
Total customer reviews: 258
Customer Reviews
Karrypto, 31 years: Should hyperbaric oxygen be added to remedy in idiopathic sudden sensorineural listening to loss Delay of surgical procedure until the kid is older may lead to a better surgical success fee. As the volume of literature has grown, presenting proof for and towards the effectiveness of interventions and the evaluation of diagnostic checks and prognosis, a new area has emerged, focused on systematically evaluating the validity of the scientific proof and summarizing the evidence.
Fedor, 24 years: Laryngopharyngeal reflux should be handled with dietary modifications such as avoiding foods that chill out the decrease esophageal sphincter and that promote acid production. The combination of pre- and post-gadolinium enhanced T1-weighted (T1W) photographs, T2-weighted (T2W) images, diffusion scanning, and fats suppression techniques helps to differentiate between various issues Table 35-3). A single switch at base pair 538 from a guanine moiety to an arginine adjustments wet wax into dry.
Gambal, 27 years: Rehabilitation with speech remedy, vocal cord medialization, and facial nerve reanimation are often effective. The strain difference deflects the cupula and the angle of the cilia within the underlying crista, affecting the firing rate of individual vestibular afferents. A long-term examine from Denmark overcame many of these obstacles by following patients over 30 years and by measuring the extrameatal tumor in a constant style.
Nemrok, 38 years: Aided speech notion talents are sometimes assessed in each monaural and binaural circumstances, relying on the usage of amplification in each ear. In addition to the above mentioned lesions, there may be many different types of benign tumors that arise from the external ear. T cells infiltrating from the systemic circulation proliferate in the endolymphatic sac.