
Privacy Disclosure Statement
Ashwagandha
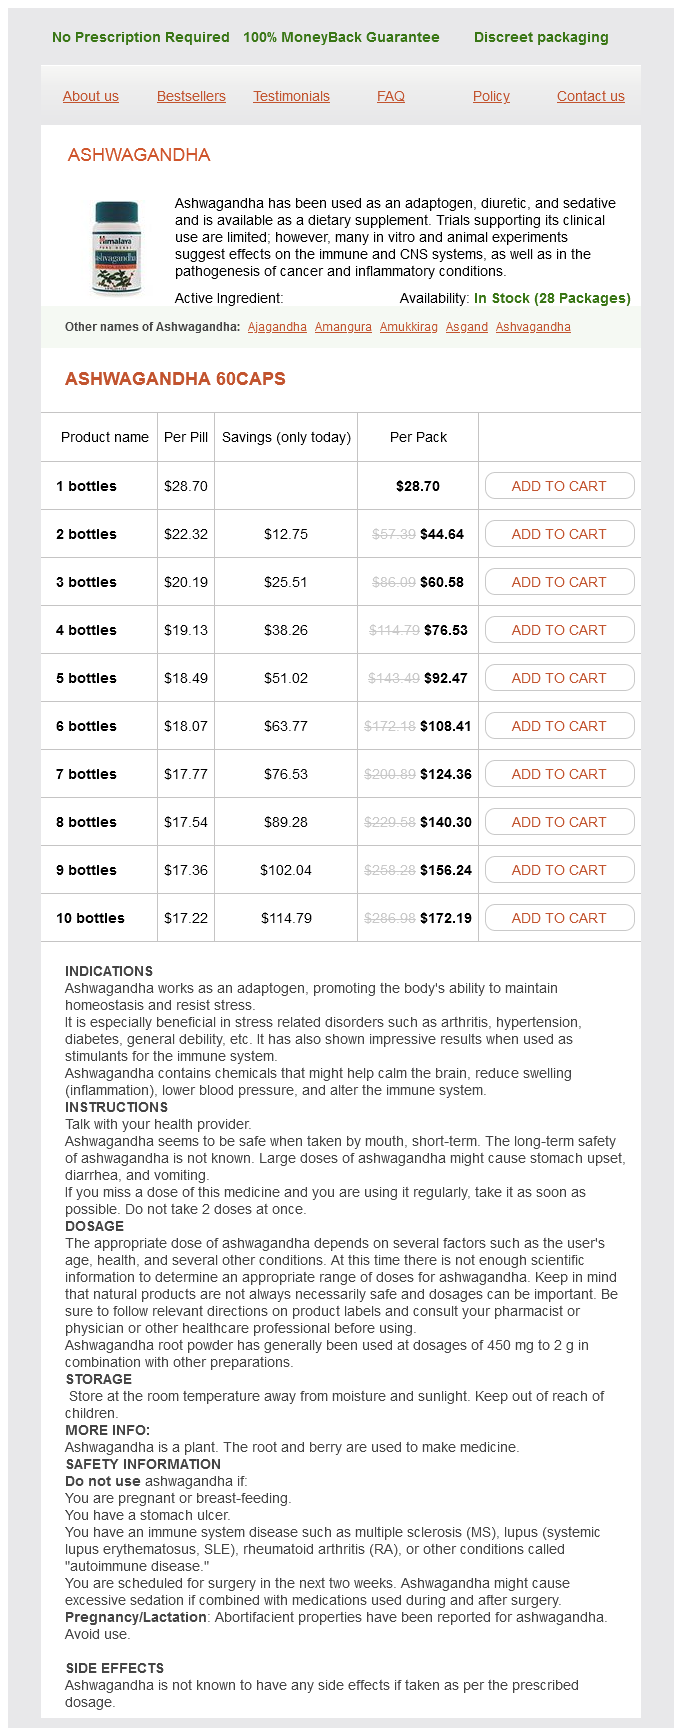
Ashwagandha 60caps
- 1 bottles - $28.70
- 2 bottles - $44.64
- 3 bottles - $60.58
- 4 bottles - $76.53
- 5 bottles - $92.47
- 6 bottles - $108.41
- 7 bottles - $124.36
- 8 bottles - $140.30
- 9 bottles - $156.24
- 10 bottles - $172.19
Ashwagandha dosages: 60 caps
Ashwagandha packs: 1 bottles, 2 bottles, 3 bottles, 4 bottles, 5 bottles, 6 bottles, 7 bottles, 8 bottles, 9 bottles, 10 bottles
Only $18,29 per item
In stock: 844
Description
Other hair products Hair bleach products incorporate peroxides anxiety 5 weeks pregnant buy ashwagandha 60 caps low cost, persulfates anxiety causes discount ashwagandha 60 caps otc, and ammonia anxiety heart rate discount 60 caps ashwagandha mastercard, which may act as major irritants anxiety 12 signs ashwagandha 60 caps cheap fast delivery. Hair bleaches Lipsticks Various R and C dyes, sunscreens, shellac, flavoring agents, preservative, and lipstick perfumes might trigger sensitization reactions. Propolis is found in lots of so-called pure merchandise, together with lip balms, toothpastes, lotions, shampoos, and different cosmetics. Eye make-up In mascara, eye shadow, and eyeliners, the preservative, shellac, metals, base wax, and perfumes are the elements which will produce sensitization, but this happens rarely. The rubber sponges used to apply eye makeup or cocamidopropylbetaine in eye makeup remover also cause eyelid dermatitis. Women nonetheless outnumber men, but as the frequency of fragrance contact reactions has elevated over time, males have proven a steeper improve in sensitivity. Fragrance is one allergen that may be transferred by skin-to-skin contact to a sensitive person, causing connubial contact dermatitis. Ingestion of balsam-related meals, such as tomatoes, citrus fruits, and spices, could trigger a flare in some sensitive patients. The alkaline permanent wave preparations, which use ammonium thioglycolate, are hardly ever if ever sensitizers and often trigger solely hair breakage and irritant reactions. The sizzling type, or acid perm, is a standard sensitizer, the allergen being glyceryl monothioglycolate. The glyceryl monothioglycolate persists within the hair for at least 3 months after application and will trigger a long-lasting dermatitis. A extra impartial pH permanent wave solution is much less allergenic than the acid perms; nonetheless, allergy to cysteamine hydrochloride found in neutral permanent wave products may happen. Hair sprays may include shellac, gum arabic, sunscreens, and artificial resins as sensitizers, and allergic reactions happen sometimes. Chemical depilatories containing calcium thioglycolate and the sulfides and sulfhydrates may cause main irritant dermatitis. Mechanical hair removers embody the mercaptans, waxes, and resins; resins may produce allergic dermatitis. Hair tonics and lotions with tincture of cinchona produce allergic sensitization; tincture of cantharidin and salicylic acid trigger main irritation. It provokes allergic reactions more regularly in therapeutic brokers utilized by atopic sufferers and in emollient products that could be used postsurgically. Dentifrices and mouthwashes Dentifrices and mouthwashes comprise sensitizers, such as the important oils used as flavoring agents, preservatives, formalin, antibiotics, and antiseptics. Circumoral dermatitis and cheilitis could additionally be caused by tartar-control kinds of dentifrice. Axillary antiperspirants Aluminum salts, such as aluminum chloride and chlorhydroxide, and zinc salts, similar to zinc chloride, act as main irritants and should rarely produce a folliculitis. Zirconium salt preparations, now faraway from all antiperspirants, produced a granulomatous response. Zirconium-aluminum complexes, nevertheless, are sometimes used as the lively ingredient in topical antiperspirants and should produce granulomas. Quaternary ammonium compounds in some roll-on deodorants could produce allergic contact dermatitis. Axillary deodorants and feminine hygiene sprays Fragrances, bacteriostats, and propellants cause nearly all of the reactions seen with these products. Deodorants that include cinnamic aldehyde can induce irritation on axillary skin even when tolerated on wholesome pores and skin in other sites. Cosmetic intolerance syndrome Occasionally, a patient will complain of intense burning or stinging after making use of any beauty. The patient often has solely subjective symptoms, however goal inflammation may also be current. The underlying cause could additionally be tough to doc, even after thorough patch, photopatch, and make contact with urticaria testing. Endogenous disease, corresponding to seborrheic dermatitis, rosacea, or atopic dermatitis, might complicate the evaluation. Avoidance of all cosmetics, with solely glycerin being allowed, for 6�12 months is commonly necessary to calm the reactive state. Adding back cosmetics separately, no extra regularly than one a week, could then be tolerated. AlrowaishdiF,etal: Allergic contact cheilitis attributable to carnauba wax in a lip balm. BroidesA,etal: Contact dermatitis with extreme scalp swelling and upper airway compromise due to black henna hair dye. EsdaileB,etal: Allergic contact dermatitis attributable to polyester-8 in a sunscreen moisturizer. HamiltonT,etal: Allergic contact dermatitis to preservatives and fragrances in cosmetics. HeisterbergM,etal: Deodorants are the leading cause of allergic contact dermatitis to fragrance elements. Jensen,P,etal: Connubial allergic contact dermatitis brought on by perfume ingredients. KindF,etal: Contact dermatitis to para-phenylenediamine in hair dye following sensitization to black henna tattoos. NardelliA,etal: Results of patch testing with fragrance mix 1, fragrance mix 2, and their elements, and Myroxylon pereirae and colophonium, over a 21-year period. Preservatives Preservatives are added to any preparation that accommodates water to kill microorganisms and stop spoilage. Such products embrace moist supplies similar to baby wipes, which when utilized in both infants or adults can produce reactions brought on by preservatives. In Euxyl K four hundred, the methyldibromoglutaronitrile part produces the allergic response. This preservative could produce false-negative outcomes on testing, so repeat open testing is indicated if a specific leave-on product is suspected of inflicting allergy. As with comparable legal guidelines regulating nickel in Europe, allergy to this preservative can also be decreasing in incidence over time. Tea tree oil is an additive to some natural products which will function an antimicrobial. It is turning into a extra frequent sensitizer as more merchandise include this oil as a "pure" antimicrobial agent. Vehicles Formulation of topically utilized products is complicated, and components are blended to make a nice base for carriage of the energetic ingredient to the pores and skin. Various emulsifiers, humectants, stabilizers, surfactants, and surface active brokers are used to make esthetically pleasing preparations. The surfactant cocamidopropyl betaine produces dermatitis of the top and neck in customers and the palms in hairdressers, often from its presence in shampoos. Formaldehyde releasers are polymers of formaldehyde that will release small amounts of formaldehyde beneath certain conditions. Allergy may be to the formaldehyde-releasing preservatives (which act as antibacterial and antifungal agents in their own right) or to the launched formaldehyde. This may be done by repetitive open utility testing to the leave-on product or by prolonged patch testing. Propylene glycol Propylene glycol is extensively used as a vehicle for topical medications, cosmetics (especially antiperspirants), and various emollient lotions. It is used within the manufacture of automobile brake fluid and alkyd resins, as a lubricant for food machinery, and as an additive for food colours and flavoring agents. Propylene glycol must be thought of as a sensitizer capable of produce contact dermatitis, and it could cause a flare of the contact dermatitis when ingested. It is examined as a 4% aqueous resolution, however irritant reactions or false-negative outcomes are common. A use check of the implicated propylene glycol� containing products could additionally be required. It may trigger contact dermatitis and cross-react with internally taken aminophylline, which consists of theophylline and ethylenediamine. SuuronenK,etal: Occupational contact allergy to cocamidopropyl betaine and its impurities. Parabens Allergic contact dermatitis might develop from parabens, that are utilized in cosmetics, meals, medicine, dentifrices, and suppositories. The paraben esters (methyl, ethyl, propyl, and butyl p-hydroxybenzoates) are used in low concentrations in cosmetics and infrequently cause dermatitis.
Pueraria thunbergiana (Kudzu). Ashwagandha.
- How does Kudzu work?
- What is Kudzu?
- Dosing considerations for Kudzu.
- Are there any interactions with medications?
- Are there safety concerns?
- Symptoms of alcohol hangover (headache, upset stomach, dizziness and vomiting), chest pains, treatment of alcoholism, menopause, muscle pain, measles, dysentery, stomach inflammation (gastritis), fever, diarrhea, thirst, cold, flu, neck stiffness, promoting sweating (diaphoretic), high blood pressure, abnormal heart rate and rhythm, stroke, and other conditions.
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96732
With the light retractor anxiety symptoms long term ashwagandha 60 caps order amex, the standard skin in- 139 Approach to the Nerves of the Lower Extremity 895 a anxiety symptoms 3 year old ashwagandha 60 caps best. More distally it innervates the extensor hallucis longus and peroneus tertius muscular tissues anxiety problems ashwagandha 60 caps on-line. The anterior tibial artery accompanies the nerve within the distal two thirds of the leg anxiety uptodate 60 caps ashwagandha order mastercard. The deep peroneal nerve emerges lateral to the tendon of the extensor hallucis longus and medial to the tendon of the extensor digitorum longus, and passes beneath the extensor retinaculum of the ankle lateral to the anterior tibial artery. The nerve branches, with its lateral branch innervating the extensor digitorum brevis and its medial branch passing underneath the tendon of the extensor hallucis brevis to innervate the primary dorsal web house. Exposure of the Superficial Peroneal Nerve the superficial peroneal nerve passes anterior to the peroneus brevis and pierces the deep fascia of the leg 10 to 12 cm above the ankle. To expose this potential website of entrapment, a linear incision is made lateral to the extensor digitorum longus from 7 to 12 cm proximal to the ankle. One of the 2 branches of the superficial peroneal nerve, the medial dorsal cutaneous nerve or the intermediate dorsal cutaneous nerve, can be identified superficial to the deep fascia and adopted proximally to where the superficial peroneal nerve pierces the fascia and passes behind the peroneal brevis muscle. The deep fascia over the nerve is divided, taking care to not injure the sural speaking and lateral cutaneous nerves as they pierce the fascia. The fibrous edges of the peroneus longus and the extensor digitorum longus are cut, exposing the bifurcation of the nerve. As with decompression of Exposure of the Deep Peroneal Nerve on the Ankle the deep peroneal nerve travels down the leg between the extensor hallucis longus and the anterior tibialis muscle tissue. An inch above the ankle, the nerve emerges lateral to the tendon of the extensor hallucis longus and medial to the ten-. The nerve continues beneath the tendon of the extensor hallucis brevis to innervate the first dorsal net area. After parting from the superficial peroneal nerve, the deep peroneal nerve passes beneath the fibrous origins of the peroneus longus and extensor digitorum longus muscles. The nerve can become entrapped under the extensor retinaculum on the ankle or under the tendon of the extensor hallucis brevis. The lateral portion of the nerve, which innervates the extensor digitorum brevis, could be biopsied to present motor fascicles. The extensor retinaculum may be cut to relieve entrapment of the distal deep peroneal nerve. A thorough understanding of the anatomy is critical to reduce potential issues. Also, minimizing disruption of regular tissues and performing a smaller, extra focal procedure decreases issues related to the approach. Conclusion There are multiple approaches for surgical procedure of the peripheral nerves of the lower extremity. Postoperative Care In addition to common wound care, postoperative care particular to peripheral nerve surgical procedure of the decrease extremity contains careful food plan development when the abdominal contents need to be manipulated and retracted as part of the method. For extra distal extremity surgical procedure, elevation of the extremity helps decrease postoperative swelling. Nerve Injuries: Operative Results for Major Nerve Injuries, Entrapments, and Tumors, 1st ed. Clin Orthop Relat Res 1977;122:255�262 Potential Complications and Precautions Complications embody nerve harm, vascular damage, injury to intra-abdominal and intrapelvic contents, compartment syn- three. Edinburgh; New York: Churchill Livingstone; 1978: 992�998 Kitagawa R, Kim D, Reid N, Kline D. Obturator nerve entrapment: prognosis and laparoscopic remedy: technical case report. The intraneural topography of the sciatic nerve and its popliteal divisions in man. Surgical publicity of the sciatic nerve in the gluteal region: anatomic and historical comparability of two approaches. The scientific significance of variations in the surgical anatomy of the superficial peroneal nerve in the mid-third of the lateral leg. The sural nerve carries mainly S1 sensory fibers and is formed primarily from two components originating from the posterior tibial (medial sural cutaneous nerve) and peroneal (lateral sural cutaneous nerve or the speaking fibular branch) in the popliteal fossa. The medial sural nerve descends deep to the gastrocnemius fascia in the proximal lower leg, working in the posterior midline, and emerges from the fascia into the subcutaneous plane about halfway down the leg, a median of 16 cm proximal to the lateral malleolus. The nerve then continues in a barely indirect course from the initial midline place down the leg on the posterior lateral aspect, then anterior to the Achilles tendon and posterior to the lateral malleolus, the place it lies in a close relation to the small saphenous vein. The normal zone of sensory innervation (and sensory loss following harm, biopsy, or nerve harvesting) is to the dorsal lateral foot. Distal to the lateral malleolus, the sural nerve runs along the lateral border of the foot and ends at the lateral side of the little toe. The sural nerve terminal branches embody the lateral dorsal cutaneous nerve and the lateral calcaneal branches. Finally, the sural nerve has an applicable anatomic makeup, together with the presence of vessels and connective tissue, a reasonable caliber and number of fascicles, and lack of intertwining fascicles over a 6- to 10-cm distance, in order that particular person fascicles may be dissected out for tease mount preparation to facilitate neuropathological interpretation. The sural nerve is most easily biopsied with the affected person in a lateral place, with the side being biopsied facing upward. The lateral decrease leg and ankle region is suitably prepped and draped, following which 1% lidocaine with 1:200,000 epinephrine is infiltrated subcutaneously in the area between the lateral malleolus and Achilles tendon. No tourniquet is used, and bipolar cautery is used for hemostasis to avoid damage to adjoining buildings. A 10-cm longitudinal skin incision is made equidistant between the lateral malleolus and the Achilles tendon, extending distally and ending simply proximal to the lateral malleolus. The sural nerve lies instantly adjacent or deep to the lesser saphenous vein at this stage. A small branch or two from the vein adjoining to the lateral malleolus might need to be coagulated and incised to facilitate nerve exposure and procurement. The decision to carry out an entire or fascicular nerve biopsy is predicated on whether or not the underlying neuropathy could have a multifocal foundation and on the severity of neuropathy. Thus, if the underlying trigger is likely to end in patchy pathology and the neuropathy is extreme, then a complete nerve biopsy must be carried out. If, however, the neuropathy is likely to outcome from a diffuse trigger, which includes all the fascicles, and the neuropathy, and therefore sensory deficit earlier than biopsy, is gentle, then a fascicular biopsy could also be carried out carefully beneath loupe magnification. The patient is then warned that the nerve is to be cut as a end result of a hundred and forty Exposure and Biopsy of the Sural Nerve 901 this step causes extreme however transient pain. For this cause, the proximal finish of the sural nerve phase being harvested is first reduce. The stump of the sural nerve remaining within the patient is allowed to retract into deep subcutaneous tissue proximal to the apex of the wound, minimizing the danger of painful neuroma formation. Then the ultimate removing of the nerve proceeds with any further distal dissection and slicing of the nerve. It is necessary not to coagulate immediately into the nerve, and to deal with it gently at all times; grasp the nerve with forceps solely at its cut end to avoid crush and harm artifact. Closure and Postoperative Care the wound is closed in layers using 2-0 or 3-0 absorbable suture on a chopping needle in a working trend for the subcutaneous tissue, and a 3-0 subcuticular suture for pores and skin closure. A strip dressing is utilized to the incision, bolstered by a 4-inch by 4-inch gauze pad and Kling rolled gauze wrapped in a circumferential style across the decrease leg and ankle to apply mild pressure. The affected person is instructed to ambulate instantly and to elevate the leg at night and when sitting. The dressing is removed after 5 days, and the incision is left exposed to air thereafter. Other Considerations and Potential Complications the time the specimen should remain in the fixing solution is predicated on laboratory protocol and varies from 5 minutes to 3 hours. Harvesting the sural nerve in midcalf permits doing a simultaneous gastrocnemius muscle biopsy. On the plus facet, there could additionally be little or no sensory loss, and the risk of a painful neuroma is lessened. With the affected person inclined, a 10-cm longitudinal incision is made in the posterior calf midline.
Specifications/Details
Once that is established anxiety symptoms depersonalization 60 caps ashwagandha purchase free shipping, sufferers must be requested about sensations of urge to defecate anxiety 4 year old ashwagandha 60 caps buy low cost, passage of solid or liquid stool anxiety worksheets for teens generic ashwagandha 60 caps line, consciousness of the episodes anxiety symptoms treatment and prevention ashwagandha 60 caps order overnight delivery, period and frequency, and presence of tenesmus and nocturnal symptoms. Finally, patients must be requested about urinary or sexual complaints as many of the causes of fecal incontinence can affect the complete pelvic flooring. A thorough medical history, including history of diabetes, neurologic disease, prior anorectal trauma or surgical procedure, and an entire obstetric historical past, must be obtained. Ask specific questions about prior deliveries, together with type, use of forceps, length of labor, measurement of child, and wish for episiotomy. Finally, medications must be reviewed, including over-the-counter medications and dietary supplements, corresponding to sorbitol (an osmotic laxative). What are necessary bodily examination characteristics to look for in sufferers with fecal incontinence Overall examination ought to include an evaluation of cognitive and different neurologic deficits as well as signs of endocrinopathies and systemic inflammatory circumstances. As with constipated sufferers, a detailed perineal and digital rectal examination should be carried out (Table 46-4). Careful attention ought to be paid to figuring out anatomic abnormalities, similar to rectal prolapse. In addition, endoscopy may be useful in detecting irritation or evaluating causes of diarrhea. The antidiarrheals, loperamide, and atropine and diphenoxylate, gradual intestinal transit. Tricyclic antidepressants can result in the side impact of constipation, to permit them to be used in incontinence for this impact. Biofeedback has been shown to be beneficial in approximately 70% of patients with pelvic floor problems. Injection of bulking brokers, corresponding to dextranomer in stabilized hyaluronic acid, remains to be in its early phases but has shown promising outcomes. Studies regarding radiofrequency ablation are primarily based on the premise that thermal lesions created in muscular tissues beneath the mucosa help in transforming and tightening throughout healing. Outcomes seem conflicting with some promising short- and long-term results, with larger studies and a sham randomized managed trial wanted. Referral to surgical procedure must be used in refractory sufferers or in those with anatomic defects, such as an external anal sphincter disruption. Transposes the gracilis muscle across the anal canal along with electrical stimulation of the muscle. Creates a stoma for severe, debilitating signs or recurrent infections in areas of skin breakdown. Primarily utilized in youngsters, but can be utilized in adults with overflow incontinence attributable to constipation. Artificial anal sphincter Anterior levatorplasty Total and postanal pelvic floor repair Rectal augmentation Fecal diversion Antegrade continence enema 38. Fecal incontinence is common in older adults and can stem from diarrhea or constipation. Cognition performs a role in continence; thus dementia in older sufferers is often a contributing factor to incontinence. In these with cognitive impairment, therapies that require active participation, such as biofeedback, may be harder. In addition restricted mobility in some older sufferers may make incontinence notably troublesome to deal with. Finally, management of decubitus ulcers and perineal pores and skin in bedbound sufferers is essential to avoiding an infection. Colonic motility in man: options in regular subjects and in sufferers with chronic idiopathic constipation. Advances in diagnostic evaluation of fecal incontinence and dyssynergic defecation. The typical scientific presentation of acute sigmoid diverticulitis consists of left lower quadrant abdominal pain associated with fever and leukocytosis. Physical examination ought to reveal tenderness within the left decrease quadrant, which could be related to guarding. The clinical presentation of diverticulitis can be atypical and generally restricted to imprecise belly ache. What is the range of severity within the medical shows of sigmoid diverticulitis It can vary from gentle, uncomplicated illness amenable to outpatient therapy to life-threatening, acute perforation of the sigmoid colon related to feculent peritonitis requiring pressing surgical treatment. The differential analysis consists of irritable bowel syndrome, inflammatory bowel disease, urologic illness, appendicitis, ischemic colitis, and colonic neoplasm (Table 47-1). A full colonoscopy ought to be performed 6 to eight weeks after decision of the episode. Other checks may be useful in particular person instances to corroborate the diagnosis (see Table 47-1). The most generally recognized surgical classification of sigmoid diverticulitis remains perhaps the Hinchey classification (Table 47-2). It is necessary to point out that the Hinchey classification was originally established on the basis of intraoperative findings and is subsequently not completely applicable to circumstances of sigmoid diverticulitis not requiring, that are the bulk. Severe diverticulitis by Ambrosetti standards is related to a risk of subsequent surgery exceeding 50%. Large arrow demonstrates sigmoid diverticulitis with colonic thickening and straining. Arrow factors to a focus of contrast extravasation and a small amount of extraluminal air. In sufferers without severe signs or significant comorbidities, an outpatient treatment is affordable. On the other hand, sufferers with extra extreme symptoms, older age, comorbidities, concerns about compliance, or concurrent immunosuppression must be preferentially admitted to the hospital. What are the antibiotic remedy choices for outpatient management of sigmoid diverticulitis Possible therapy options embrace broad-spectrum penicillin, a mix of either fluoroquinolone, cephalosporin or trimethoprim-sulfamethoxazole with metronidazole, and clindamycin (Table 47-4). Orders for patients admitted for acute sigmoid diverticulitis ought to embrace nothing by mouth and rehydration with intravenous fluids, while additionally receiving intravenous antibiotics. In this respect, attainable brokers include broad-spectrum penicillins or cephalosporins. A mixture of a fluoroquinolone and metronidazole is a broadly used different, notably in patients allergic to penicillin. Rarely used but acceptable alternatives, especially in the critically ill patient, embody carbapenems (see Table 47-4). What is the pure history of diverticulitis following the primary assault of uncomplicated illness The overwhelming majority of hospitalized sufferers experience enchancment of their condition in the course of the first forty eight hours following admission. However, roughly 10% to 15% exhibit medical deterioration requiring surgery during the identical hospital keep. Serial scientific examinations and monitoring of the laboratory values are important to promptly identify patients unresponsive to medical administration. Once the affected person recovers from the primary uncomplicated disease assault managed conservatively, as much as one third of sufferers might experience recurrent diverticulitis after 10 years. Neither seeds nor nuts have been proven to be dangerous in patients with prior diverticulitis. It has been instructed that no much less than some circumstances of diverticulitis are actually the manifestation of a selected subtype of inflammatory bowel dysfunction and may acquire advantage from therapy with antiinflammatory brokers (mesalamine). What are the current indications for surgical procedure in uncomplicated sigmoid diverticulitis, and have they developed over time Recurrent severe assaults of diverticulitis occurring in short intervals should be thought-about for surgery. Mild assaults of recurrent diverticulitis occurring in lengthy intervals could additionally be managed expectantly and not require surgical intervention after the second episode. In this case you will want to plan for a proper left colectomy somewhat than sigmoidectomy. On the other hand, diverticulitis of the cecum or proper colon is extra frequent and has a clinical presentation similar to acute appendicitis. Regardless of its particular location, uncomplicated colonic diverticulitis ought to be initially treated with antibiotics. What are the chance components implicated in illness recurrence after a diverticulitis attack Stricture, fistula, abscess, and peritonitis are an important complications of sigmoid diverticulitis. Phlegmon has been mentioned for example of sophisticated diverticulitis but remains a considerably arbitrary definition. More hardly ever, the sigmoid inflammation can extend into the retroperitoneum and trigger ureteral obstruction, mostly on the left aspect. Prior hysterectomy increases the chance for diverticulitisrelated colovaginal fistula. The cornerstone within the administration of sophisticated diverticulitis stays surgical procedure, unless the patient has prohibitive comorbidities.
Additional information:
Syndromes
- What medicines do you take?
- Adults should get help from family or friends before making important decisions. This is because reasoning and thinking processes may be impaired.
- Foods like bread, grains, beans, rice, pasta, and starchy vegetables are loaded with vitamins, minerals, fiber, and healthy carbohydrates.
- Methotrexate
- Injury to the lung, which could cause more breathing problems
- Weakness
- Forced vital capacity (FVC)
- Blue fingernails and lips
- 24 hours: 8 - 25%
- Penicillins
Related Products
Usage: q.3h.
Tags: ashwagandha 60 caps with mastercard, purchase 60 caps ashwagandha fast delivery, purchase 60 caps ashwagandha with amex, ashwagandha 60 caps buy with amex, ashwagandha 60 caps order otc, ashwagandha 60 caps purchase without prescription, cheap ashwagandha 60 caps, cheap 60 caps ashwagandha with amex, buy generic ashwagandha 60 caps on-line, ashwagandha 60 caps order fast delivery, 60 caps ashwagandha generic with mastercard, ashwagandha 60 caps cheap on line, ashwagandha 60 caps purchase otc, generic ashwagandha 60 caps otc, quality 60 caps ashwagandha, ashwagandha 60 caps cheap with mastercard
9 of 10
Votes: 225 votes
Total customer reviews: 225
Customer Reviews
Inog, 52 years: The inheritance sample is recessive and involves a mutation from glutamic acid to glutamine at amino acid residue 474 (Glu474Gln) on at least one allele. Atherosclerosis generally entails the femoral artery, which is often the positioning of entry for the angiographic catheter. In some cases refractory to topical brokers, intralesional or systemic corticosteroid therapy could also be required.
Irhabar, 55 years: A branching and tapering gasoline pattern in the liver, if predominantly near the hilum (arrowheads), usually is biliary (A) however sometimes is in portal veins. Once the acute process is controlled, corticosteroids are tapered (usually over 2 to 3 weeks) as a result of they, alone or in combination with cytotoxic medication, can improve viral replication. Heavy publicity of commercial staff to chromates might produce chrome ulcers on the backs of the palms and forearms, usually beginning around a hair follicle, or within the creases of the knuckles or finger webs.
Ingvar, 36 years: A mixture of systemic antibiotics and percutaneous drainage has become the treatment of choice for the management of pyogenic liver abscess. LeppingP,etal: Antipsychotic therapy of major delusional parasitosis: systematic review. In addition to the subclavian artery, the brachial plexus travels between the anterior and middle scalene muscles in the thoracic outlet.
Karrypto, 44 years: Practice Guidelines Committee of the American Association for the Study of Liver Diseases. The choice between these procedures is individualized based on the underlying pathology, affected person characteristics, and surgeon preference, although nerve transection is mostly nicely tolerated and is more profitable in reaching long-term symptomatic reduction. Closure and Postoperative Care the wound is closed in layers utilizing 2-0 or 3-0 absorbable suture on a slicing needle in a running trend for the subcutaneous tissue, and a 3-0 subcuticular suture for skin closure.