
Privacy Disclosure Statement
Allegra
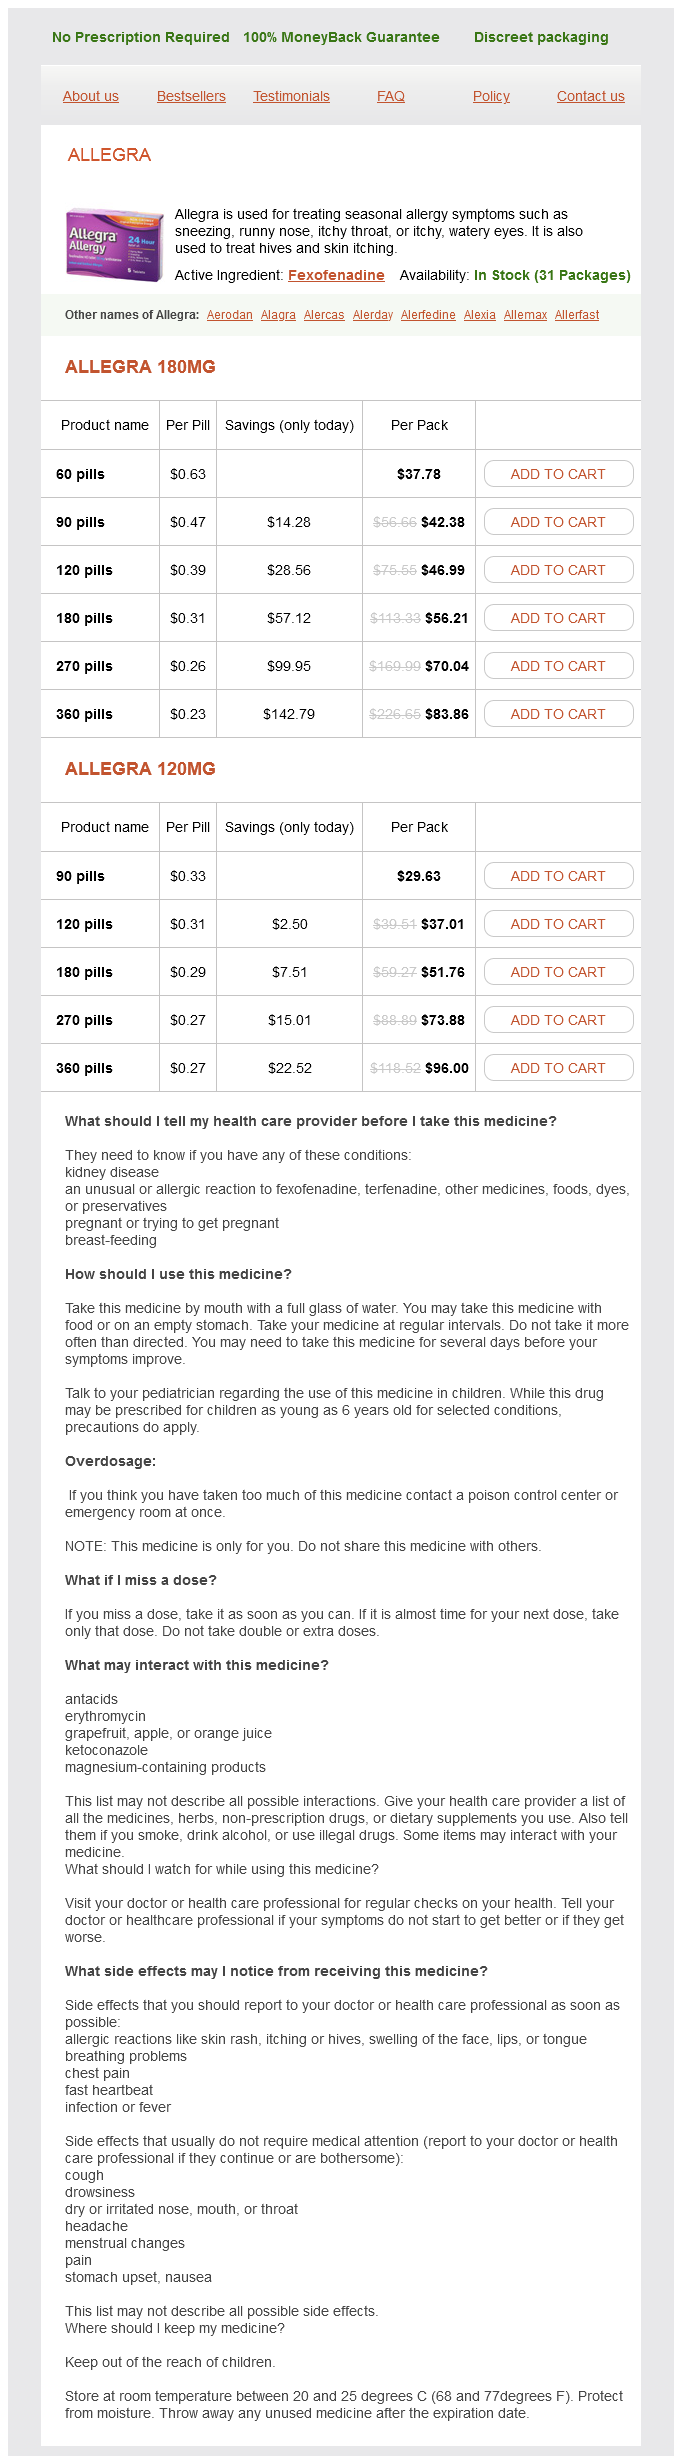
Allegra 180mg
- 60 pills - $37.78
- 90 pills - $42.38
- 120 pills - $46.99
- 180 pills - $56.21
- 270 pills - $70.04
- 360 pills - $83.86
Allegra 120mg
- 90 pills - $29.63
- 120 pills - $37.01
- 180 pills - $51.76
- 270 pills - $73.88
- 360 pills - $96.00
Allegra dosages: 180 mg, 120 mg
Allegra packs: 60 pills, 90 pills, 120 pills, 180 pills, 270 pills, 360 pills
Only $0,23 per item
In stock: 760
Description
In one patient on this group allergy shots reactions swelling allegra 180 mg discount amex, a nodule of the stomach wall was excised allergy shots for dust mites allegra 180 mg cheap with amex, however the tumor recurred 1 yr after remedy allergy shots lymphoma cheap 120 mg allegra fast delivery. These knowledge point out that epithelioid hemangioendotheliomas of bone pursue an indolent course and can be controlled by restricted surgical procedure allergic pink eye allegra 120 mg generic without prescription, radiofrequency ablation,126 and radiotherapy. A, Epithelioid endothelial cells forming poorly developed vascular channels, cords, and nests in a chondroid-like stroma. B, Higher magnification of A exhibits epithelioid endothelial cells forming cords and nests in chondroid-like stroma. D, Higher magnification of C exhibits solid sheets of epithelioid endothelial cells with poorly developed vascular spaces. A and B, Low power photomicrographs showing solid sheets and small nests of epithelioid endothelial cells. C and D, Higher power photomicrographs displaying stable sheets and nests of epithelioid endothelial cells sometimes forming poorly developed small vascular areas. A, Low energy magnification of pattern of plump, epithelioid cells arranged in cords in basophilic myxoid stroma. B, Higher magnification shows attribute intracytoplasmic vacuoles in epithelioid endothelial cells. A and B, Low power photomicrographs present overall nodular structure of this epithelioid hemangioendothelioma. A, Solid nests of epithelioid endothelial cells with anastomosing vascular sample. B, Higher magnification of A shows densely packed epithelioid endothelial cells with distinct cytoplasmic borders. A, B, and D, Strong reactivity of epithelial endothelioid cells with Ulex europaeus lectin. A, Anastomosing sample of vessels lined by distinguished epithelial endothelial cells. B, Ultrastructure of crowded epithelioid endothelial cells that line vascular channel. B, Higher magnification of A shows cytoplasms of two endothelial cells related by tight junctions. Inset documents densely packed intermediate filaments consistent with vimentin within cytoplasm of endothelial cell. This rare tumor occurs predominantly in the superficial soft tissue (subcutis and dermis) of distal parts of the extremities, significantly in the hand. The low power microscopic options embody the presence of enormous vascular areas with thrombosis and adjoining proliferation of blunt spindle cells. The spindle cells also can merge with cavernous vessels that proliferate within the thickened intervascular septa. In addition, the cranial lesions also contained foci of epithelioid endothelial cells. Originally, spindle-cell hemangioendotheliomas have been thought-about to be low-grade malignant tumors. The two patients in our series who had spindle-cell hemangioendothelioma of bone are free of illness 5 and 7 years after curettage. In fact, a quantity of latest research from different institutions additionally advanced this idea. In the previous, such phrases as malignant hemangioendothelioma and hemangioendothelial sarcoma of bone had been used interchangeably with angiosarcoma. Definition Angiosarcoma is an intermediate- to high-grade malignant tumor composed of atypical endothelial cells that have vasoformative features. Data from the Surveillance, Epidemiology, and End Results study point out that lower than 2% of main bone sarcomas had been categorized as angiosarcomas. Like low-grade vascular tumors, they can be multicentric, involving multiple bones of the lower extremity. This might clarify the early statement that multicentric malignant vascular tumors of bone appear to have a greater prognosis. The disparity could also be extra related to better differentiation than to multicentricity. Angiosarcomas of bone have been noticed to happen as secondary malignancies in bone infarcts,one hundred forty four,a hundred and fifty in fibrous dysplasia,164 and after publicity to external irradiation. The vascular nature of the lesion may be suspected on radiographs if synchronous multicentric involvement of a quantity of bones of one extremity or of one anatomic region is present. Microscopic Findings the tumor consists of atypical endothelial cells and displays vasoformative options. Angiosarcomas arising at different websites and in different organs have some distinct options and are considered separate clinicopathologic entities. They occur most incessantly in the dermis and subcutis, particularly within the head and neck area. Chronic lymphatic stasis is a well known predisposing situation for angiosarcoma of the dermis and delicate tissue. A, Lateral radiograph of skull of a 19-year-old girl with multifocal lytic lesions of frontal and parietal regions. C, Axial magnetic resonance picture with gadolinium enhancement exhibits both frontal and parietal lesions. A, Low powered view exhibits two components of tumor: vascular and solid spindle cells. B, Higher magnification of strong spindle-cell space composed of interlacing bundles of plump spindle cells. D, Interference between vascular and spindle-cell parts reveals spindle-cell proliferation in septa of vascular spaces. Destruction by tumor of distal tibial shaft with cortical breakthrough laterally and slight periosteal new bone formation. A and B, Low and better power photomicrographs displaying irregular anastomosing vascular channels lined by extremely atypical endothelial cells. C and D, Irregular anastomosing vascular spaces and solid areas of extremely atypical spin cell proliferations. A and B, Low and excessive power photomicrographs displaying anastomosing vascular channels lined by highly atypical endothelial cells. C and D, Low and high power photomicrographs exhibiting irregular anastomosing channels and stable glomeruloid proliferations of highly atypical endothelial cells inside vascular areas. A and B, Low and intermediate power photomicrographs present poorly developed anastomosing vascular spaces and stable areas of spindle cell proliferations. C and D, Intermediate and high power photomicrographs exhibiting irregular anastomosing vascular areas lined by highly atypical endothelial cells. A and B, Intermediate and high power photomicrographs exhibiting vascular areas lined by extremely atypical epithelioid endothelial cells forming often strong nodules. C and D, High power photomicrographs exhibiting vascular channels lined by highly atypical epithelioid endothelial cells forming loosely arranged nodules. Note single epithelioid cells dispersed in stromal tissue mimicking metastatic carcinoma. A and B, Low and intermediate power photomicrographs exhibiting irregular cystlike vascular areas and proliferations of atypical endothelial cells forming septations and cords. C and D, High power photomicrograph exhibiting extremely atypical epithelioid cells forming solid nests, cords, and septations. Large solid areas of endothelial cells that mimic an epithelial neoplasm may be current. Intermediate-grade, well-differentiated angiosarcomas may have better developed vascular channels and exhibit much less pronounced atypia of endothelial cells. In much less differentiated areas missing apparent vasoformative features, endothelial marker reactivity may be very focal or absent. In distinction with low-grade endothelial bone neoplasms, epithelial markers (epithelial membrane antigen and cytokeratins) are much less frequently current. The absence of cytokeratin reactivity and powerful reactions to antibodies for vimentin helps to distinguish these tumors from carcinomas of the spindle-cell kind. Distinguishing lower-grade angiosarcomas from epithelioid hemangioendothelioma is discussed in the part on the differential prognosis for that neoplasm, but coexistence of epithelioid hemangioendothelioma and epithelioid angiosarcoma in the same lesion is feasible. Treatment and Behavior High-grade angiosarcomas exhibit extremely aggressive behavior with speedy native progress and early disseminated metastases. Some lesions have a less aggressive scientific course, however the prognosis in a group of patients with high-grade angiosarcomas is poor as a end result of these tumors have a excessive propensity for metastases.
Ayuk Willku (Maca). Allegra.
- >Anemia, leukemia, chronic fatigue syndrome (CFS), enhancing energy and athletic performance, improving memory, depression, female hormone imbalance, menstrual problems, infertility, menopause symptoms, osteoporosis, stomach cancer, tuberculosis, sexual problems, immune system stimulation, AIDS, and other conditions.
- Enhancing sexual desire in men.
- What other names is Maca known by?
- Are there safety concerns?
- Dosing considerations for Maca.
- How does Maca work?
- What is Maca?
Source: http://www.rxlist.com/script/main/art.asp?articlekey=96554
Giant cell tumor might occur extra frequently in Chinese folks than in individuals who stay in Western countries allergy forecast venice italy 180 mg allegra otc. The estimated price within the Chinese inhabitants has been reported to account for about 20% of all main tumors of bone allergy medicine zyrtec coupons allegra 120 mg discount amex. Radiographic Imaging the radiographic picture of an enormous cell tumor is kind of attribute and diagnostic if current in the particular anatomic website of skeletally mature patients allergy medicine urinary retention allegra 180 mg order on-line. In a small proportion of circumstances allergy testing knoxville tn purchase allegra 180 mg otc, there could be minimal periosteal reaction when the cortex is breached. These adjustments could be correlated with the microscopic findings of extensive reactive fibrohistiocytic features (see later section). Peak age incidence and frequent websites of skeletal involvement in giant cell tumor. A and B, Anteroposterior and lateral plain radiographs present involvement of lateral condyle. A, Radiograph of knee of an 18-yearold skeletally mature woman with large cell tumor involving lateral tibial plateau and lengthening into metaphysis. B, Photomicrograph of curetted tibial lesions shows even distribution of large cells in spindle-cell stroma (�100). D, Computed tomogram of tumor proven in C clearly demonstrates dense cortexlike rim surrounding tumor. A and B, Radiographs of right knee of a 31-year-old man who fell and sustained displaced pathologic fracture by way of medial cortex as properly as midarticular floor of femur. C and D, Anteroposterior and lateral radiographs of distal femoral giant cell tumor with impacted pathologic fracture. Patient was a 40-yearold man who noticed aching ache and slight swelling above his knee for 1 year. A, Anteroposterior radiograph of distal femoral big cell tumor with impacted pathologic fracture. C, Radiograph of left knee of a 54-year-old lady who had pins placed in distal femoral fracture 1 year beforehand. Fact that big cell tumor was present was not appreciated, and tumor grew into gentle tissue around femur. D, Coronally bisected amputation specimen of case shown in C with big cell tumor inside fractured distal femur and adjoining delicate tissue. The quiescent type is characterised by a lytic defect restricted to the medullary cavity of the bone with minimal or no involvement of the cortical bone. Usually the defect is surrounded by a roughly clear rim of sclerosis, and fantastic trabeculation may be present. The lively radiologic type is characterised by a thinned, expanded cortex and considerably unclear margins. The aggressive radiologic sort is characterized by a lytic defect with ill-defined margins, invasion of the cortex, and extension of the tumor into surrounding delicate tissue. These are clinically irrelevant and misleading phrases as a result of they overlap with phrases used to describe histologic options. Radiologic features of aggressiveness with huge damaging lesions, massive invasion into the cortex, and extension of the tumor into surrounding gentle tissue are merely reflections of the stage of the illness. Overlap in radiologic presentation with fibrosarcoma, malignant fibrous histiocytoma, multiple myeloma, and different harmful lesions can happen. Nonepiphyseal localization of the lesion sometimes occurs in skeletally mature patients. So-called nonepiphyseal large cell tumor represents a medical curiosity and is extraordinarily rare. The tumor tissue is properly demarcated and usually extends to the articular cartilage. The lesion usually occupies an eccentric position in the epiphyseal end of the bone. It is delimited in its periphery by a thin layer of fibrous and reactive bone tissue. The cortical bone will not be concerned, and the unique contour of the bone could also be preserved. However, extra regularly, the original cortex has been destroyed, and the bone contour has been expanded. A thin shell of subperiosteal bone surrounding the periphery of the lesion is typically seen. There additionally may be proof of pathologic fracture, most frequently involving the subchondral bony endplate. They are round or oval with regular outlines, evenly distributed fine chromatin, and a outstanding nucleolus. In addition to these two cell populations, occasional binucleated and trinucleated cells can be seen, suggesting a gradual transition of some mononuclear cells into multinucleated large cells. This phenomenon could be seen notably properly in cytologic preparations by which whole intact cells are analyzed. Giant cells often have dense eosinophilic cytoplasm with clear, sharp, oval borders. All these sort of cells may be current in a single tumor, sometimes accounting for a superficial impression of pleomorphism. The basic account of the histologic criteria for the diagnosis of giant cell tumors by Jaffe et al. This early histologic description included a numeric grading system (grades 1 by way of 3) that was designed to predict recurrent conduct and metastatic potential. Subsequent experience has shown that the use of numeric histologic grading lacks predictive worth. The traditional microscopic pattern of big cell tumor is regularly modified by a secondary reactive proliferation of fibrohistiocytic tissue, hemorrhage, necrosis, and aneurysmal bone cyst formation. Reactive fibrous tissue with a prominent storiform sample and xanthogranulomatous response may be documented, no less than focally, in nearly all appropriately sampled lesions. A, Anteroposterior radiograph of large cell tumor in skeletally immature patient reveals no involvement of epiphysis. B, Lateral view of tumor shown in A shows no extension to secondary development middle. C, Lateral radiograph of distal femur of a 27-year-old woman with pain in lower thigh. D, T1-weighted magnetic resonance image shows that big cell tumor seen in C is restricted to shaft. E, Bisected distal radial resection specimen showing an expansile multilocular giant cell tumor composed of darkish and light-weight tan tissue with focal yellowish areas. A, Anteroposterior radiograph exhibiting an expansile lytic lesion of the proximal fibula with fantastic trabecular sample. B, Bisected proximal fibula resection specimen displaying an expansile big cell tumor with multilocular cystic architecture. A, Bisected distal femoral resection specimen shows light and dark tan big cell tumor with marbling fibrous tissue. Mild growth of the bone contour with intact cortex and sharp demarcation of the tumor from the surrounding medullary bone is current. B, Expansile big cell tumor of distal femur composed of sunshine and darkish tan tissue with central fibronecrotic areas. C, Giant cell tumor of tibia extending to the articular plate and expanding the bone contour laterally. D, A giant expansile big cell tumor of the proximal humerus composed of sunshine and darkish tan tissue. Large areas of yellowish necrotic tissue in the central portion of the lesion are present. B, Posterior aspect of specimen proven in A shows destroyed cortex and growth of tumor into popliteal fossa. C, Bisected distal end of radius with well-demarcated eccentric tumor mass expanding bone contour.
Specifications/Details
A allergy diagnosis purchase allegra 180 mg fast delivery, Sharp demarcation of two distinct tumor elements: standard chordoma (left) and high-grade spindle-cell sarcoma (right) allergy treatment dallas 120 mg allegra overnight delivery. Muller H: Ueber das Vorkommen von Resten der Chorda dorsalis bei Menschen nach der Geburt und uber-ihr Verhaltnis zu den Gallert-geschwulsten am Clivus allergy symptoms like the flu order 120 mg allegra overnight delivery. Virchow R: Untersuchungen ueber die Entwicklung des Schaedelgrundes cat allergy symptoms yahoo order allegra 180 mg fast delivery, Berlin, 1857, G Rimer. Yamaguchi T, Yamato M, Saotome K: First histologically confirmed case of a classic chordoma arising in a precursor benign notochordal lesion: differential analysis of benign and malignant notochordal lesions. Auger M, Raney B, Callender D, et al: Metastatic intracranial chordoma in a baby with huge pulmonary tumor emboli. Differential Diagnosis Conventional chordoma may present outstanding nuclear atypia focally or diffusely or may mimic an epithelial neoplasm. Dedifferentiated chondrosarcoma has very comparable architectural options to conventional chordomas. The difference is in a low-grade precursor lesion that has options of conventional chordoma and that coexpresses S-100 protein and epithelial markers. Attention to the radiographic findings and location of the lesion within the sites typical for chordoma are essential in guiding the selection of a biopsy web site that would come with both attainable tumor components. Treatment and Behavior Dedifferentiation can occur in major or recurrent chordomas. However, in some instances, a transient response to aggressive chemotherapy protocols has been reported. Horwitz T: the human notochord: a examine of its improvement and regression-variations and pathologic derivative chordoma, Indianapolis, 1977, limited non-public printing. Kuroda H, Inui M, Sugimoto K, et al: Axial protocadherin is a mediator of prenotochord cell sorting in xenopus. Azzarelli A, Quagliuolo V, Cerasoli S, et al: Chordoma: natural history and remedy results in 33 circumstances. Barresi V, Ieni A, Branca G, et al: Brachyury: a diagnostic marker for the differential diagnosis of chordoma and hemangioblastoma versus neoplastic histological mimickers. Dalpra L, Malgara R, Miozzo M, et al: First cytogenetic research of a recurrent familial chordoma of the clivus. Gottschalk D, Fehn M, Patt S, et al: Matrix gene expression evaluation and mobile phenotyping in chordoma reveals focal differentiation sample of neoplastic cells mimicking nucleus pulposus growth. Kubota T, Sato K, Kabuto M, et al: Immunohistochemical and ultrastructural examine of cranium base chordomas. Mertens F, Kreicbergs A, Rydholm A, et al: Clonal chromosome aberrations in three sacral chordomas. Miller J: Relationship of the notochord to the cartilage of the skull and its correlation with the placement and frequencies of chordomata. Mori K, Chano T, Kushima R, et al: Expression of E-cadherin in chordomas: diagnostic marker and attainable role of tumor cell affinity. Presneau N, Shalaby A, Ye H, et al: Role of the transcription factor T (brachyury) in the pathogenesis of sporadic chordoma: a genetic and functional-based study. Shen J, Shi Q, Lu J, et al: Histological research of chordoma origin from fetal notochordal cell rests. Moriki T, Takahashi T, Wada M, et al: Chondroid chordoma: fine-needle aspiration cytology with histopathological, immunohistochemical, and ultrastructural study of two cases. Vujovic S, Henderson S, Presneau N, et al: Brachyury, a vital regulator of notochordal improvement, is a novel biomarker for chordomas. Halpern J, Kopolovic J, Catane R: Malignant fibrous histiocytoma developing in irradiated sacral chordoma. Vanel D, Rebibo G, Hales H, et al: Contribution of computed tomography in six sacrococcygeal chordomas. Hasegawa M, Nishijima W, Watanabe I, et al: Primary chondroid chordoma arising from the base of the temporal bone: a 10-year post-operative follow-up. Miettinen M: Chordoma: antibodies to epithelial membrane antigen and carcinoembryonic antigen in differential diagnosis. Although most metastases encountered in the grownup skeleton are either carcinoma or melanoma, sarcomas may metastasize to bone, particularly within the pediatric population. The basic surgical pathologist is far more more likely to encounter a skeletal focus of metastatic most cancers than any of the primary malignant bone tumors. Patients regularly current with signs and symptoms associated to metastatic bone lesions before a major tumor has come to clinical consideration, and severe ache or a pathologic fracture is usually the presenting criticism. Despite the customarily in depth immunohistochemical analysis of metastatic deposits, a primary supply may be elusive and typically never positioned. The incidence and localization, radiologic characteristics, patterns of spread, and histologic and immunohistochemical options of assorted metastatic lesions in bone are thought of in some detail in this chapter. Because fine-needle aspiration cytology performs a serious role in diagnosing metastatic lesions affecting the skeleton, we embody in this chapter a quick description of cytologic options of metastatic tumors in bone. First, nonetheless, you will want to discuss a number of the newer information on the biology of tumor metastasis that has been derived from the strategies of molecular pathology. This info is essential for lots of reasons, including the understanding of the pharmacologic methods for treating bone metastases. The primary biology, molecular mechanisms, and genetic and epigenetic modifications that drive these steps are extremely complicated and probably differ depending on the source of the metastasis and specific type of tumor. Before metastasizing, tumor cells put together distant websites to receive metastatic deposits by creating a premetastatic niche. Those tumor cells which may be able to survive in transit turn out to be lodged in capillaries within a secondary web site similar to bone, adhere to the endothelium, and ultimately extravasate through the capillary wall and into the stroma, the place they proliferate and in the end form clinically vital plenty. A, To metastasize, tumor cells should gain several unique biologic properties such as invasive growth, induction of vascular growth, vascular invasion, adherence to endothelial cells or thrombosis of peripheral sinusoids, continuation of invasive development with extravasation, and formation of main and secondary metastatic foci. Although biologic phenomena related to tumor progression and metastasis are often current as sequence of orderly occasions, in actuality tumor cells might develop these properties in a virtually haphazard pattern. Moreover, not all tumor cells might develop all properties listed; some cell clones might subspecialize. B, Summary of molecular changes associated with tumor cell interaction with numerous stromal elements important for invasive development and metastasis. Integrins, a superfamily of transmembrane receptors that modulate cell-tocell and cell-to-matrix interactions by binding with a selection of ligands, play a key function in skeletal metastases on many ranges, matrix and blood vessel invasion, osteoclast signaling, neovascularization, and colonization of bone. Thus the interplay of tumor cells with extracellular matrix appears to be one of many major mechanisms of the metastatic cascade. The basement membrane is a sheetlike structure that separates epithelial and endothelial cells from the interstitial matrix. This giant advanced molecule has three short arms containing collagen binding websites and a single lengthy arm with a heparan binding web site. The central region of the molecule, where all four arms are connected in a cross-shaped construction, incorporates the laminin receptor binding web site for cells. A, Both systemic elements and domestically performing elements induce the formation and activity of osteoclasts. Accessory cells similar to T cells can produce cytokines that may inhibit the formation of osteoclasts, similar to interleukin-4, interleukin-18 and interferon-. B, Both systemic components and domestically performing elements can improve the proliferation and differentiation of osteoblasts. In addition, bone matrix is a serious source of growth elements, which might improve the proliferation and differentiation of osteoblasts. Fibronectin is one of the major noncollagenous parts of the interstitial matrix. To invade the intercellular matrix and to penetrate the vascular channels, the tumor cells should observe three basic steps: 1. They must keep some extent of their attachment to the matrix components (mainly laminin and fibronectin). Degradation of the matrix parts must proceed via the motion of proteolytic enzymes. Tumor cells must proceed to migrate into the degraded area of the extracellular matrix. Paradoxically, it has been shown that tumor cells exhibiting elevated ranges of laminin and fibronectin floor receptors have the next metastatic potential compared with those that have minimal ranges of these receptors.
Additional information:
Syndromes
- Thrombolytics to dissolve an existing clot
- Infections in the bone marrow (very rare)
- Adolescent pregnancy
- Decreased air entry into the lungs
- Fainting or feeling light-headed
- Heart attack
- Seems irritable
- Asthma
- NSAIDs, such as ibuprofen, for joint symptoms and pleurisy
Related Products
Usage: p.o.
Tags: buy discount allegra 180 mg online, cheap 180 mg allegra visa, buy 180 mg allegra free shipping, safe 180 mg allegra, allegra 180 mg buy mastercard, generic allegra 180 mg fast delivery, allegra 180 mg buy without a prescription, 180 mg allegra free shipping, allegra 120 mg on-line, 180 mg allegra best, allegra 180 mg buy free shipping, allegra 180 mg generic with visa, buy 180 mg allegra mastercard, purchase 180 mg allegra with visa, allegra 180 mg cheap amex, allegra 120 mg purchase on line
10 of 10
Votes: 38 votes
Total customer reviews: 38
Customer Reviews
Varek, 61 years: Note ill-defined irregular interface between the hyaline cartilage areas and undifferentiated element.
Angir, 21 years: B, Lateral view of tumor proven in A shows no extension to secondary progress heart.
Gancka, 35 years: The involvement of several completely different proteases, together with urokinase, plasminogen activator, cathepsins B and D, and numerous metalloproteases produced instantly by tumor cells, play an important position within the invasive progress and growth of metastasis.
Dimitar, 26 years: The much less cellular myxoid portions of the tumor are characterized by the presence of hydrated proteoglycans and solely minor amounts of collagens.
Miguel, 44 years: Multinucleated large cells are virtually at all times present and are sparsely distributed among the different elements.
Diego, 54 years: For these reasons, biopsy of a solitary renal mass in a patient with lymphoma is performed to distinguish a renal metastasis from a primary renal malignancy.
Frillock, 37 years: Chondromyxoid fibroma is an eccentric metaphyseal lesion with scalloped margins, fine trabeculations, and intact cortex.
Dolok, 65 years: In monostotic fibrous dysplasia, the proximal femoral shaft is involved in roughly 40% of patients, adopted by the tibia (15%), humerus (5%), and radius (5%).